


Few molecules have changed the conversation around metabolism as quickly as glucagon-like peptide-1 (GLP-1) and its synthetic analogs. In a little over a decade, GLP-1 receptor agonists went from a niche diabetes therapy to one of the most studied drug classes in the world. Along the way, they became a central tool for researchers trying to understand how the gut, brain, and pancreas coordinate appetite, glucose, and energy balance.
This article explains what GLP-1 is, how peptide analogs such as semaglutide were engineered, what the research record shows, and where important questions remain. It is written for readers who want the science rather than the hype.
What GLP-1 Is And Why It Matters
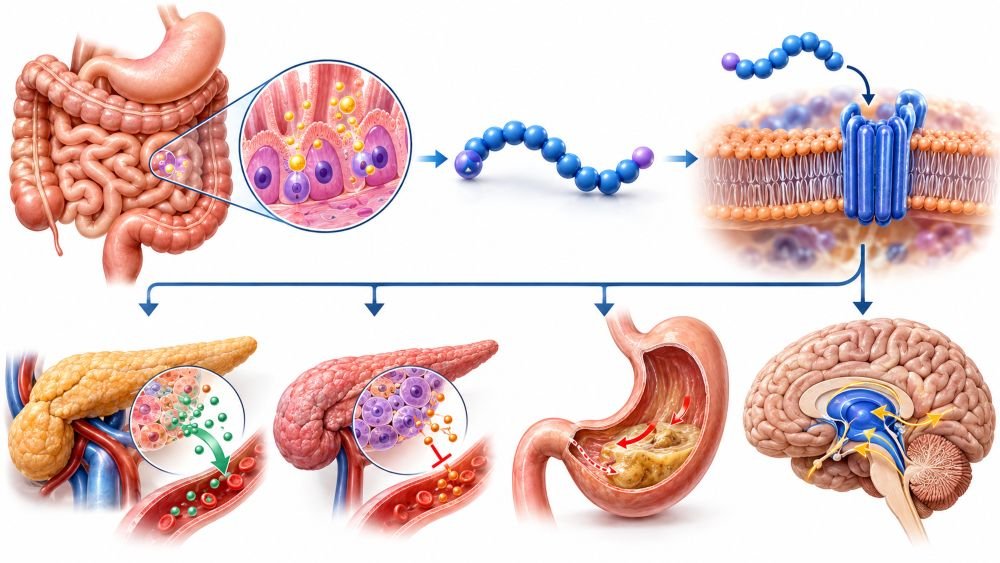
GLP-1 is a 30-amino-acid hormone produced by L-cells in the lining of the small intestine and colon. It is released within minutes of eating, in response to nutrients reaching the gut. Together with glucose-dependent insulinotropic polypeptide (GIP), it belongs to the incretin family: gut hormones that amplify insulin secretion after a meal.
GLP-1 acts through the GLP-1 receptor, a G protein–coupled receptor found on pancreatic beta cells, in several brain regions, in the stomach, the heart, and other tissues. When the receptor is activated, cyclic AMP rises inside the cell and a cascade of signaling follows. The best-documented effects, drawn from decades of physiology research, include:
- Glucose-dependent insulin release. GLP-1 stimulates insulin secretion only when blood glucose is elevated, which is why the pathway attracted interest as a safer way to lower glucose than agents that act regardless of glucose level.
- Suppression of glucagon. GLP-1 reduces secretion of glucagon, the hormone that raises blood glucose, again in a glucose-dependent manner.
- Slowed gastric emptying. Food leaves the stomach more slowly, which blunts the post-meal glucose spike.
- Central effects on appetite. GLP-1 receptors in the hypothalamus and brainstem are involved in satiety signaling. In animal studies, activating them reduces food intake.
The catch is that native GLP-1 is fragile. The enzyme dipeptidyl peptidase-4 (DPP-4) cleaves it within one to two minutes of release, removing the first two amino acids and inactivating it. That short half-life makes the native hormone nearly useless as a research tool or therapeutic on its own. The solution was to engineer analogs that resist DPP-4.
How Semaglutide Was Engineered
Semaglutide is a modified version of human GLP-1 with three deliberate changes, each solving a specific problem:
- Position 8: alanine → α-aminoisobutyric acid (Aib). This unnatural amino acid blocks DPP-4 from cleaving the N-terminus.
- Position 34: lysine → arginine. This removes one of two lysines so that the fatty-acid chain attaches at a single, defined site.
- Position 26: a C18 fatty diacid attached via a linker. The fatty-acid chain binds tightly but reversibly to albumin in the bloodstream. Albumin acts as a circulating reservoir that protects the peptide from degradation and kidney clearance.
The result, described by Lau and colleagues in the Journal of Medicinal Chemistry in 2015, is a peptide with a half-life of roughly one week in humans, compared with minutes for native GLP-1. The albumin-binding strategy had already been proven in liraglutide, an earlier analog with a C16 fatty acid and a daily dosing schedule; semaglutide extended it to once-weekly.
For researchers, this engineering history is instructive. It shows how small, targeted modifications to a natural peptide can transform its pharmacokinetics without changing which receptor it activates.
What Preclinical Research Shows
Animal and cell studies built the foundation for everything that followed. Several lines of evidence stand out.
- Appetite and food intake. In rodents, GLP-1 receptor agonists consistently reduce food intake and body weight. Work by Secher and colleagues (2014, Journal of Clinical Investigation) used fluorescently labeled liraglutide to show that the peptide reaches the hypothalamus and acts on specific neuron populations, including pro-opiomelanocortin (POMC) neurons that promote satiety. Later studies with semaglutide found similar access to brain regions involved in feeding behavior.
- Body weight and fat mass. In diet-induced obese mice, semaglutide reduced body weight primarily by lowering energy intake rather than by raising energy expenditure. Gabery and colleagues (2021, JCI Insight) mapped where semaglutide binds in the mouse brain and found it reached several hypothalamic and brainstem nuclei involved in appetite regulation, acting through circumventricular organs rather than crossing the blood-brain barrier.
- Beta-cell function. In cultured islets and rodent models, GLP-1 receptor activation improves glucose-stimulated insulin secretion and, in some models, supports beta-cell survival. Translating the survival findings to humans has proven difficult, which is a reminder that rodent islets and human islets do not always behave alike.
- Cardiovascular and other tissues. GLP-1 receptors are expressed in the heart and vasculature. Preclinical work has reported effects on blood pressure, inflammation, and cardiac function, which helped motivate later clinical outcome trials.
These findings are what make a semaglutide peptide valuable in a laboratory setting: it is a well-characterized tool for probing GLP-1 receptor biology in cell and animal models, with a large literature to compare against.
What Clinical Research Shows
The clinical record for semaglutide is unusually deep because it was developed as a pharmaceutical and tested in large, randomized trials. Summarizing the key results, with the caveat that these are findings in specific patient populations under medical supervision:
- SUSTAIN program (type 2 diabetes). Across multiple phase 3 trials, once-weekly semaglutide reduced HbA1c and body weight compared with placebo and active comparators in adults with type 2 diabetes.
- STEP 1 (Wilding et al., 2021, New England Journal of Medicine). In 1,961 adults with obesity or overweight and at least one weight-related condition, but without diabetes, 68 weeks of semaglutide 2.4 mg plus lifestyle intervention produced a mean weight change of −14.9 percent versus −2.4 percent with placebo.
- SELECT (Lincoff et al., 2023, NEJM). In 17,604 adults with established cardiovascular disease and overweight or obesity, semaglutide reduced the rate of major adverse cardiovascular events by 20 percent over a mean follow-up of about 40 months.
Gastrointestinal effects were the most common adverse events across trials: nausea, diarrhea, vomiting, and constipation, usually during dose escalation.
Semaglutide is approved by the FDA under the brand names Ozempic (type 2 diabetes), Wegovy (chronic weight management and, since 2024, cardiovascular risk reduction in adults with cardiovascular disease and obesity or overweight), and Rybelsus (an oral formulation for type 2 diabetes). These are prescription medicines used under medical supervision.
Research Peptides And Approved Drugs Are Not The Same Thing

This distinction matters and is worth stating plainly.
Pharmaceutical semaglutide is manufactured under Good Manufacturing Practice, formulated for injection, sterility-tested, and dispensed with a prescription. Research-grade semaglutide is a chemical reagent sold to laboratories for in vitro and animal studies. It is not sterile-formulated for human use, is not FDA-approved, and is labeled for research only. The FDA has stated that semaglutide products should be obtained only by prescription from licensed pharmacies, and has flagged compounded and counterfeit products as a safety concern.
The appropriate use of a research peptide is in the lab: receptor binding assays, cell signaling studies, animal models of metabolism, and analytical method development. The quality markers that matter in that setting are purity by HPLC, identity by mass spectrometry, and a batch-specific certificate of analysis. A generic peptide supplier that publishes those documents for every lot gives researchers what they need to interpret results with confidence.
GLP-1 In Context: Other Peptide Axes
GLP-1 analogs are one tool among many for studying metabolism. Researchers often compare or combine them with peptides acting on other systems:
- Dual and triple agonists. Tirzepatide activates both GLP-1 and GIP receptors. Retatrutide adds glucagon receptor activity. These newer molecules test whether engaging multiple incretin pathways produces effects beyond GLP-1 alone.
- Growth hormone axis. GHRH analogs such as sermorelin and mod grf act on the pituitary rather than the gut-brain axis. They are studied for their effects on growth hormone secretion and body composition through an entirely separate mechanism.
- Amylin analogs. Amylin is co-secreted with insulin and also slows gastric emptying and reduces food intake. Combinations of amylin and GLP-1 analogs are under active investigation.
Keeping these mechanisms distinct helps researchers design cleaner experiments and avoid attributing an effect to the wrong pathway.
Open Questions
Despite the volume of research, several questions remain unresolved:
- Lean mass. Weight loss in clinical trials included a meaningful proportion of lean mass alongside fat mass. How to preserve muscle during GLP-1-driven weight loss is an active research area.
- Durability. Weight regain after discontinuation was substantial in extension studies, suggesting the effect depends on continued receptor activation rather than a lasting reset of body-weight regulation.
- Mechanism of appetite effects. Which neuron populations and brain circuits mediate reduced food intake, and whether central and peripheral receptors contribute differently, is still being mapped.
- Long-term effects. Trials to date run a few years. The consequences of decade-long GLP-1 receptor activation are not yet known.
These are exactly the kinds of questions that preclinical research with well-characterized peptides is designed to address.
FAQ
What Does GLP-1 Actually Do In The Body?
It is a gut hormone released after eating that increases insulin secretion when glucose is high, lowers glucagon, slows stomach emptying, and signals satiety to the brain.
Why Does Semaglutide Last So Much Longer Than Natural GLP-1?
Three modifications protect it: an unnatural amino acid that blocks enzyme breakdown, and a fatty-acid chain that binds to albumin in the blood, which shields the peptide and slows its clearance.
Is A Research-Grade Semaglutide The Same As Ozempic Or Wegovy?
No. The approved drugs are sterile pharmaceutical formulations dispensed by prescription. Research-grade material is a laboratory reagent for in vitro and animal studies and is not intended for human use.
What Is The Difference Between GLP-1 Analogs And GHRH Analogs?
They act on different systems. GLP-1 analogs work on the incretin pathway (gut, pancreas, brain). GHRH analogs work on the pituitary to influence growth hormone. They are studied for different questions.
References
- Drucker DJ. Mechanisms of action and therapeutic application of glucagon-like peptide-1. Cell Metab. 2018;27(4):740–756.
- Lau J, Bloch P, Schäffer L, et al. Discovery of the once-weekly glucagon-like peptide-1 (GLP-1) analogue semaglutide. J Med Chem. 2015;58(18):7370–7380.
- Secher A, Jelsing J, Baquero AF, et al. The arcuate nucleus mediates GLP-1 receptor agonist liraglutide-dependent weight loss. J Clin Invest. 2014;124(10):4473–4488.
- Gabery S, Salinas CG, Paulsen SJ, et al. Semaglutide lowers body weight in rodents via distributed neural pathways. JCI Insight. 2021;6(6):e133429.
- Wilding JPH, Batterham RL, Calanna S, et al. Once-weekly semaglutide in adults with overweight or obesity. N Engl J Med. 2021;384(11):989–1002.
- Lincoff AM, Brown-Frandsen K, Colhoun HM, et al. Semaglutide and cardiovascular outcomes in obesity without diabetes. N Engl J Med. 2023;389(24):2221–2232.
- Nauck MA, Quast DR, Wefers J, Meier JJ. GLP-1 receptor agonists in the treatment of type 2 diabetes: state-of-the-art. Mol Metab. 2021;46:101102.
- U.S. Food and Drug Administration. FDA’s concerns with unapproved GLP-1 drugs used for weight loss. FDA.gov.
Disclaimer: For research use only. Not for human consumption. This content is for informational purposes and is not medical advice. Research-grade peptides are laboratory reagents intended for in vitro and animal studies only; they are not FDA-approved and must not be used in humans. Approved semaglutide medicines are prescription products that should only be used under the supervision of a licensed healthcare provider. External links are shared for reference only, and their inclusion does not imply endorsement of any product, company, or service.